INDICATION: TIVDAK® is indicated for the treatment of adult patients with recurrent or metastatic cervical cancer (r/mCC) with disease progression on or after chemotherapy.

Watch these helpful videos for treatment tips and guidance from healthcare professionals

These doctors and nurses have years of experience working with teams who treat cervical cancer. Here, they discuss Tivdak’s clinical profile and share their experience with Tivdak.

When to Consider Tivdak

Dr. Dana M. Chase discusses the unmet needs in cervical cancer and when to consider Tivdak for your eligible patients.

Insights from the innovaTV 301
Clinical Trial

Insights from the innovaTV 301 Clinical Trial

Dr. Dana Chase reviews the innovaTV 301 clinical study, and efficacy and safety profile of Tivdak.

PEERspectives: Effective Care Coordination

Dr. Thomas Krivak and Nurse Practitioner Courtney Arn discuss coordinating as a team to deliver patient-first care.

PEERspectives: An Eye on Tivdak

Dr. Thomas Krivak and Dr. Kayla Campbell talk about ocular adverse reactions in oncology.

Get an in-depth look at the Tivdak mechanism of action
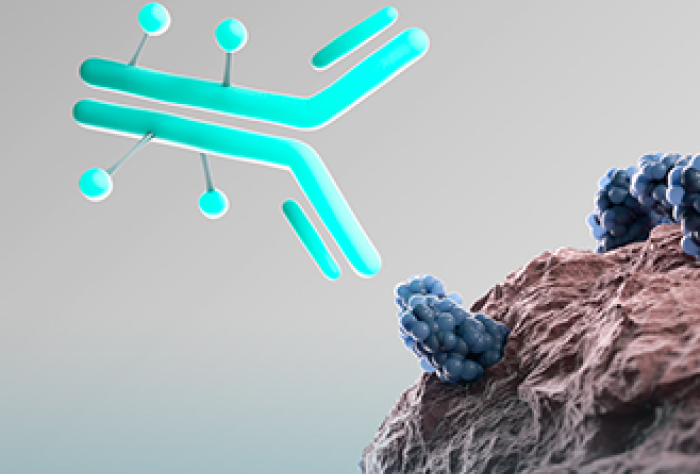
Tivdak® (tisotumab vedotin-tftv) molecule in representation of the Tivdak proposed mechanism of action

See phase 3 clinical trial results

Woman standing in front of wall filled with pictures and a few empty picture frames

Get to know the Tivdak infusion cycle
Woman looking at drip from an infusion.

Explore the Tivdak Mechanism of Action

  • Discover a different approach with Tivdak (tisotumab vedotin-tftv)—the first and only antibody-drug conjugate, or ADC, that targets Tissue Factor (TF).

    Indication

    TIVDAK is indicated for the treatment of adult patients with recurrent or metastatic cervical cancer (r/mCC) with disease progression on or after chemotherapy.

    BOXED WARNING: OCULAR TOXICITY

    TIVDAK can cause severe ocular toxicities resulting in changes in vision, including severe vision loss, and corneal ulceration. Conduct an ophthalmic exam, including an assessment of ocular symptoms, visual acuity, and slit lamp exam of the anterior segment of the eye prior to initiation of TIVDAK, prior to every cycle for the first nine cycles, and as clinically indicated. Adhere to the required premedication and eye care before, during, and after infusion. Withhold TIVDAK until improvement and resume, reduce the dose, or permanently discontinue, based on severity.

    Please see additional Important Safety Information at the end of this video and full prescribing information, including BOXED WARNING for TIVDAK, at tivdakHCP.com.

    Tivdak is an ADC offering a different approach to previously treated recurrent or metastatic cervical cancer.

    Let’s take a deeper look and explore the Tivdak mechanism of action.

    Tivdak was designed with 3 components: a novel, fully human monoclonal antibody directed against a cell surface protein called Tissue Factor.

    Tissue Factor is prevalent on cervical cancer cells and is also present on some epithelial cells.

    Nonclinical data suggest Tissue Factor-expression is associated with cancer pathophysiology and tumor development.

    The second component of Tivdak is the cytotoxic agent, monomethyl auristatin E, or MMAE, a potent microtubule disruptor, and the third component is a protease-cleavable linker that attaches the cytotoxic agent to the monoclonal antibody.

    Each component plays a crucial role in the Tivdak mechanism of action.

    Nonclinical data suggest the anticancer activity of Tivdak is a result of Tivdak binding to Tissue Factor–expressing cells.

    Then the Tivdak and Tissue Factor complex is internalized and trafficked to the lysosomes, and MMAE is released from the antibody via proteolytic cleavage.

    MMAE disrupts the microtubule network of actively dividing cells.

    This disruption leads to cell cycle arrest and apoptosis.

    In vitro, Tivdak also mediates antibody-dependent cellular phagocytosis and antibody-dependent cellular cytotoxicity.

    With ADC technology, Tivdak provides the potency of a cytotoxic agent, combined with the specificity of an antibody, which gives you the opportunity to try a different approach when treating your eligible patients.

    Indication

    TIVDAK is indicated for the treatment of adult patients with recurrent or metastatic cervical cancer (r/mCC) with disease progression on or after chemotherapy.

    Important Safety Information

    BOXED WARNING: OCULAR TOXICITY

    TIVDAK can cause severe ocular toxicities resulting in changes in vision, including severe vision loss, and corneal ulceration. Conduct an ophthalmic exam, including an assessment of ocular symptoms, visual acuity, and slit lamp exam of the anterior segment of the eye prior to initiation of TIVDAK, prior to every cycle for the first nine cycles, and as clinically indicated. Adhere to the required premedication and eye care before, during, and after infusion. Withhold TIVDAK until improvement and resume, reduce the dose, or permanently discontinue, based on severity.

    Warnings and Precautions

    Ocular adverse reactions: TIVDAK can cause severe ocular adverse reactions, including conjunctivitis, keratopathy (keratitis, punctate keratitis, and ulcerative keratitis), and dry eye (increased lacrimation, eye pain, eye discharge, pruritus, irritation, and foreign body sensation), that may lead to changes in vision and/or corneal ulceration.

    Ocular adverse reactions occurred in 55% of patients with cervical cancer treated with TIVDAK across clinical trials. The most common were conjunctivitis (32%), dry eye (24%), keratopathy (17%), and blepharitis (5%). Grade 3 ocular adverse reactions occurred in 3.3% of patients, including severe ulcerative keratitis in 1.2% of patients. Nine patients (2.1%) experienced ulcerative keratitis (including one with perforation requiring corneal transplantation), six (1.4%) conjunctival ulcer, four (0.9%) corneal erosion, two (0.5%) conjunctival erosion, and two (0.5%) symblepharon.

    In innovaTV 301, 8 patients (3.2%) experienced delayed ocular adverse reactions occurring more than 30 days after discontinuation of TIVDAK. These adverse reactions included 3 patients with ulcerative keratitis, and one patient (each) with keratitis, punctate keratitis and corneal erosion, blepharitis and conjunctival hyperemia, conjunctival scar, and conjunctivitis and xerophthalmia.

    Refer patients to an eye care provider to conduct an ophthalmic exam prior to initiation of TIVDAK, prior to every cycle for the first nine cycles, and as clinically indicated. The exam should include visual acuity, slit lamp exam of the anterior segment of the eye, and an assessment of normal eye movement and ocular signs or symptoms which include dry or irritated eyes, eye secretions, or blurry vision.

    Adhere to the required premedication and eye care before, during, and after infusion to reduce the risk of ocular adverse reactions. Monitor for ocular toxicity and promptly refer patients to an eye care provider for any new or worsening ocular signs and symptoms. Withhold, reduce, or permanently discontinue TIVDAK based on the severity or persistence of the ocular adverse reaction.

    Peripheral neuropathy (PN) occurred in 39% of cervical cancer patients treated with TIVDAK across clinical trials; 6% of patients experienced Grade 3 PN. PN adverse reactions included peripheral sensory neuropathy (23%), PN (5%), paresthesia (3.8%), peripheral sensorimotor neuropathy (3.3%), muscular weakness (2.8%), and peripheral motor neuropathy (2.4%). One patient with another tumor type treated with TIVDAK at the recommended dose developed Guillain-Barre syndrome.

    Monitor patients for signs and symptoms of neuropathy such as paresthesia, tingling or a burning sensation, neuropathic pain, muscle weakness, or dysesthesia. For new or worsening PN, withhold, then dose reduce, or permanently discontinue TIVDAK based on the severity of PN.

    Hemorrhage occurred in 51% of cervical cancer patients treated with TIVDAK across clinical trials. The most common all grade hemorrhage adverse reaction was epistaxis (33%). Grade 3 hemorrhage occurred in 4% of patients.

    Monitor patients for signs and symptoms of hemorrhage. For patients experiencing pulmonary or central nervous system hemorrhage, permanently discontinue TIVDAK. For Grade ≥2 hemorrhage in any other location, withhold until bleeding has resolved, blood hemoglobin is stable, there is no bleeding diathesis that could increase the risk of continuing therapy, and there is no anatomical or pathologic condition that can increase the risk of hemorrhage recurrence. After resolution, either resume treatment or permanently discontinue TIVDAK.

    Pneumonitis that is severe, life-threatening, or fatal can occur in patients treated with antibody-drug conjugates containing vedotin, including TIVDAK. Among cervical cancer patients treated with TIVDAK across clinical trials, 4 patients (0.9%) experienced pneumonitis, including 1 patient who had a fatal outcome.

    Monitor patients for pulmonary symptoms of pneumonitis. Symptoms may include hypoxia, cough, dyspnea or interstitial infiltrates on radiologic exams. Infectious, neoplastic, and other causes for such symptoms should be excluded through appropriate investigations. Withhold TIVDAK for patients who develop persistent or recurrent Grade 2 pneumonitis and consider dose reduction. Permanently discontinue TIVDAK in all patients with Grade 3 or 4 pneumonitis.

    Severe cutaneous adverse reactions (SCAR), including events of fatal or life-threatening Stevens-Johnson syndrome (SJS), can occur in patients treated with TIVDAK. SCAR occurred in 1.6% of cervical cancer patients treated with TIVDAK across clinical trials. Grade ≥3 SCAR occurred in 0.5% of patients, including 1 patient who had a fatal outcome.

    Monitor patients for signs or symptoms of SCAR, which include target lesions, worsening skin reactions, blistering or peeling of the skin, painful sores in mouth, nose, throat, or genital area, fever or flu-like symptoms, and swollen lymph nodes. If signs or symptoms of SCAR occur, withhold TIVDAK until the etiology of the reaction has been determined. Early consultation with a specialist is recommended to ensure greater diagnostic accuracy and appropriate management. Permanently discontinue TIVDAK for confirmed Grade 3 or 4 SCAR, including SJS.

    Embryo-fetal toxicity: TIVDAK can cause fetal harm when administered to a pregnant woman. Advise patients of the potential risk to a fetus. Advise females of reproductive potential to use effective contraception during treatment with TIVDAK and for 2 months after the last dose. Advise male patients with female partners of reproductive potential to use effective contraception during treatment with TIVDAK and for 4 months after the last dose.

    Adverse Reactions

    Across clinical trials of TIVDAK in 425 patients with r/mCC, the most common (≥25%) adverse reactions, including laboratory abnormalities, were hemoglobin decreased (45%), PN (39%), conjunctival adverse reactions (38%), nausea (37%), fatigue (36%), aspartate aminotransferase increased (33%), epistaxis (33%), alopecia (31%), alanine aminotransferase increased (30%), and hemorrhage (28%).

    innovaTV 301 Study: 250 patients with r/mCC with disease progression on or after systemic therapy

    Serious adverse reactions occurred in 33% of patients receiving TIVDAK; the most common (≥2%) were urinary tract infection (4.8%), small intestinal obstruction (2.4%), sepsis, abdominal pain, and hemorrhage (each 2%). Fatal adverse reactions occurred in 1.6% of patients who received TIVDAK, including acute kidney injury, pneumonia, sepsis, and SJS (each 0.4%).

    Adverse reactions leading to permanent discontinuation occurred in 15% of patients receiving TIVDAK; the most common (≥3%) were PN and ocular adverse reactions (each 6%). Adverse reactions leading to dose interruption occurred in 39% of patients receiving TIVDAK; the most common (≥3%) were ocular adverse reactions (16%) and PN (6%). Adverse reactions leading to dose reduction occurred in 30% of patients receiving TIVDAK; the most common (≥3%) were PN and ocular adverse reactions (each 10%). The ocular adverse reactions included conjunctival disorders (4.8%), keratopathy (4%), and dry eye (0.8%).

    innovaTV 204 Study: 101 patients with r/mCC with disease progression on or after chemotherapy

    Serious adverse reactions occurred in 43% of patients; the most common (≥3%) were ileus (6%), hemorrhage (5%), pneumonia (4%), PN, sepsis, constipation, and pyrexia (each 3%). Fatal adverse reactions occurred in 4% of patients who received TIVDAK, including septic shock, pneumonitis, sudden death, and multisystem organ failure (each 1%).

    Adverse reactions leading to permanent discontinuation occurred in 13% of patients receiving TIVDAK; the most common (≥3%) were PN (5%) and corneal adverse reactions (4%). Adverse reactions leading to dose interruption occurred in 47% of patients; the most common (≥3%) were PN (8%), conjunctival adverse reactions, and hemorrhage (each 4%). Adverse reactions leading to dose reduction occurred in 23% of patients; the most common (≥3%) were conjunctival adverse reactions (9%) and corneal adverse reactions (8%).

    Drug Interactions

    Strong CYP3A4 inhibitors: Concomitant use with strong CYP3A4 inhibitors may increase unconjugated monomethyl auristatin E (MMAE) exposure, which may increase the risk of TIVDAK adverse reactions. Closely monitor patients for TIVDAK adverse reactions.

    Use in Specific Populations

    Moderate or severe hepatic impairment: MMAE exposure and adverse reactions are increased. Avoid use.

    Lactation: Advise lactating women not to breastfeed during TIVDAK treatment and for at least 3 weeks after the last dose.

    Please see full Prescribing Information, including BOXED WARNING for TIVDAK, at tivdakHCP.com.

Insights from the innovaTV 301 Clinical Trial

  • Dr. Chase:

    Hello, I’m Dr. Dana Chase. Today I’ll be reviewing the clinical study, efficacy, and safety profile of Tivdak (tisotumab vedotin-tftv), an antibody-drug conjugate for the treatment of adult patients with recurrent or metastatic cervical cancer with disease progression on or after chemotherapy.

    Please stay tuned for full Important Safety Information at the end of this video and see the full Prescribing Information linked on this site. Let’s get started.

    VOICE OVER:

    TIVDAK is indicated for the treatment of adult patients with recurrent or metastatic cervical cancer (r/mCC) with disease progression on or after chemotherapy.

    SELECT IMPORTANT SAFETY INFORMATION

    BOXED WARNING: OCULAR TOXICITY

    TIVDAK can cause severe ocular toxicities resulting in changes in vision, including severe vision loss, and corneal ulceration. Conduct an ophthalmic exam, including an assessment of ocular symptoms, visual acuity, and slit lamp exam of the anterior segment of the eye prior to initiation of TIVDAK, prior to every cycle for the first nine cycles, and as clinically indicated. Adhere to the required premedication and eye care before, during, and after infusion. Withhold TIVDAK until improvement and resume, reduce the dose, or permanently discontinue, based on severity.

    Please stay tuned for full Important Safety Information at the end of this video and see the full Prescribing Information, including BOXED WARNING, linked on this site or at tivdakHCP.com.

    Dr. Chase:

    innovaTV 301 included 502 patients with recurrent or metastatic cervical cancer who had received 1 or 2 prior systemic therapy regimens. In this study, 253 patients received Tivdak 2 mg per kg every 3 weeks and 249 patients received investigator’s choice chemotherapy, which was representative of the standard of care at that time. The primary endpoint in this trial was overall survival, which is clinically relevant for a second-line or later cervical cancer trial. Key secondary endpoints included progression-free survival, objective response rate, and safety. Also, determination of Tissue Factor expression was not required for enrollment.

    The innovaTV 301 trial studied a broad range of patients and included patients with squamous cell carcinomas, adenocarcinomas, and adenosquamous carcinomas. Additionally, over 30% of patients received 2 prior lines of therapy, meaning they were heavily pretreated. Also, these days the majority of our recurrent patients have had anti-PD-1 or anti- PD-L1 exposure and the innovaTV 301 trial included patients that had received prior checkpoint inhibitor therapy.

    Before we look at efficacy data for Tivdak, let’s review some Important Safety Information.

    VOICE OVER:

    Select Important Safety Information for Tivdak includes Warnings and Precautions for peripheral neuropathy, hemorrhage, pneumonitis, severe cutaneous adverse reactions, and embryo-fetal toxicity.

    Please stay tuned for full Important Safety Information at the end of this video and see the full Prescribing Information, including BOXED WARNING, linked on this site or at tivdakHCP.com.

    Dr. Chase:

    As I mentioned earlier, the primary endpoint of the trial was overall survival.

    The median overall survival was 11.5 months with Tivdak versus 9.5 months with investigator’s choice chemotherapy. Therefore, Tivdak was proven to extend survival versus investigator’s choice chemotherapy. When I see that patient with recurrent second-line disease it can be a tricky conversation, meaning we’re frequently at that point talking to the patient about survival. When I consider these data, I also look at risk reduction. It’s clinically meaningful to me that there was a 30% reduction in the risk of death with the use of Tivdak compared to investigator’s choice chemotherapy.

    The overall survival results for Tivdak are further bolstered by the objective response rate in innovaTV 301. Tivdak demonstrated a superior overall response rate of 17.8% versus 5.2% with investigator’s choice chemotherapy. This means that over 3 times as many patients taking Tivdak achieved a partial or complete response versus chemotherapy. Even partial response can be meaningful to my patients because they’ve already progressed on at least one line of therapy.

    On the innovaTV 301 trial there was a statistically significant improvement in progression-free survival. The median PFS was 4.2 months for Tivdak versus 2.9 months for investigator’s choice chemotherapy and the P value for that was less than 0.0001. Some patients ask me how long before their tumor grows again, and I tell them that every patient is different and sometimes it’s very hard to explain to them the results of a clinical trial. But on this innovaTV 301 trial, the median was about four months with Tivdak compared to three months with traditional chemotherapy.

    Ocular toxicity, for which Tivdak has a boxed warning, was one of the more common all-grade toxicities associated with Tivdak. Tivdak has a premedication and required Eye Care plan that can help reduce the risk of ocular adverse reactions. Because of the innovaTV 301 trial and the results of that trial, Tivdak has become an important part of the treatment landscape for patients with recurrent second-line or greater disease.

    It really expands options for patients after they progress on first-line therapy. As a provider who understands the poor prognosis of advanced cervical cancer, I appreciate Tivdak because it allows me to continue discussions with patients about the next steps in their treatment journeys.

    I’d like to thank those of you who joined me today and encourage you to stay tuned for the full Important Safety Information.

    VOICE OVER:

    Important Safety Information

    BOXED WARNING: OCULAR TOXICITY

    TIVDAK can cause severe ocular toxicities resulting in changes in vision, including severe vision loss, and corneal ulceration. Conduct an ophthalmic exam, including an assessment of ocular symptoms, visual acuity, and slit lamp exam of the anterior segment of the eye prior to initiation of TIVDAK, prior to every cycle for the first nine cycles, and as clinically indicated. Adhere to the required premedication and eye care before, during, and after infusion. Withhold TIVDAK until improvement and resume, reduce the dose, or permanently discontinue, based on severity.

    Warnings and Precautions

    Ocular adverse reactions: TIVDAK can cause severe ocular adverse reactions, including conjunctivitis, keratopathy (keratitis, punctate keratitis, and ulcerative keratitis), and dry eye (increased lacrimation, eye pain, eye discharge, pruritus, irritation, and foreign body sensation), that may lead to changes in vision and/or corneal ulceration.

    Ocular adverse reactions occurred in 55% of patients with cervical cancer treated with TIVDAK across clinical trials. The most common were conjunctivitis (32%), dry eye (24%), keratopathy (17%), and blepharitis (5%). Grade 3 ocular adverse reactions occurred in 3.3% of patients, including severe ulcerative keratitis in 1.2% of patients. Nine patients (2.1%) experienced ulcerative keratitis (including one with perforation requiring corneal transplantation), six (1.4%) conjunctival ulcer, four (0.9%) corneal erosion, two (0.5%) conjunctival erosion, and two (0.5%) symblepharon.

    In innovaTV 301, 8 patients (3.2%) experienced delayed ocular adverse reactions occurring more than 30 days after discontinuation of TIVDAK. These adverse reactions included 3 patients with ulcerative keratitis, and one patient (each) with keratitis, punctate keratitis and corneal erosion, blepharitis and conjunctival hyperemia, conjunctival scar, and conjunctivitis and xerophthalmia.

    Refer patients to an eye care provider to conduct an ophthalmic exam prior to initiation of TIVDAK, prior to every cycle for the first nine cycles, and as clinically indicated. The exam should include visual acuity, slit lamp exam of the anterior segment of the eye, and an assessment of normal eye movement and ocular signs or symptoms which include dry or irritated eyes, eye secretions, or blurry vision.

    Adhere to the required premedication and eye care before, during, and after infusion to reduce the risk of ocular adverse reactions. Monitor for ocular toxicity and promptly refer patients to an eye care provider for any new or worsening ocular signs and symptoms. Withhold, reduce, or permanently discontinue TIVDAK based on the severity or persistence of the ocular adverse reaction.

    Peripheral neuropathy (PN) occurred in 39% of cervical cancer patients treated with TIVDAK across clinical trials; 6% of patients experienced Grade 3 PN. PN adverse reactions included peripheral sensory neuropathy (23%), PN (5%), paresthesia (3.8%), peripheral sensorimotor neuropathy (3.3%), muscular weakness (2.8%), and peripheral motor neuropathy (2.4%). One patient with another tumor type treated with TIVDAK at the recommended dose developed Guillain-Barre syndrome.
    Monitor patients for signs and symptoms of neuropathy such as paresthesia, tingling or a burning sensation, neuropathic pain, muscle weakness, or dysesthesia. For new or worsening PN, withhold, then dose reduce, or permanently discontinue TIVDAK based on the severity of PN.

    Hemorrhage occurred in 51% of cervical cancer patients treated with TIVDAK across clinical trials. The most common all grade hemorrhage adverse reaction was epistaxis (33%). Grade 3 hemorrhage occurred in 4% of patients.

    Monitor patients for signs and symptoms of hemorrhage. For patients experiencing pulmonary or central nervous system hemorrhage, permanently discontinue TIVDAK. For Grade ≥2 hemorrhage in any other location, withhold until bleeding has resolved, blood hemoglobin is stable, there is no bleeding diathesis that could increase the risk of continuing therapy, and there is no anatomical or pathologic condition that can increase the risk of hemorrhage recurrence. After resolution, either resume treatment or permanently discontinue TIVDAK.

    Pneumonitis that is severe, life-threatening, or fatal can occur in patients treated with antibody-drug conjugates containing vedotin, including TIVDAK. Among cervical cancer patients treated with TIVDAK across clinical trials, 4 patients (0.9%) experienced pneumonitis, including 1 patient who had a fatal outcome.

    Monitor patients for pulmonary symptoms of pneumonitis. Symptoms may include hypoxia, cough, dyspnea or interstitial infiltrates on radiologic exams. Infectious, neoplastic, and other causes for such symptoms should be excluded through appropriate investigations. Withhold TIVDAK for patients who develop persistent or recurrent Grade 2 pneumonitis and consider dose reduction. Permanently discontinue TIVDAK in all patients with Grade 3 or 4 pneumonitis.

    Severe cutaneous adverse reactions (SCAR), including events of fatal or life-threatening Stevens-Johnson syndrome (SJS), can occur in patients treated with TIVDAK. SCAR occurred in 1.6% of cervical cancer patients treated with TIVDAK across clinical trials. Grade ≥3 SCAR occurred in 0.5% of patients, including 1 patient who had a fatal outcome.

    Monitor patients for signs or symptoms of SCAR, which include target lesions, worsening skin reactions, blistering or peeling of the skin, painful sores in mouth, nose, throat, or genital area, fever or flu-like symptoms, and swollen lymph nodes. If signs or symptoms of SCAR occur, withhold TIVDAK until the etiology of the reaction has been determined. Early consultation with a specialist is recommended to ensure greater diagnostic accuracy and appropriate management. Permanently discontinue TIVDAK for confirmed Grade 3 or 4 SCAR, including SJS.

    Embryo-fetal toxicity: TIVDAK can cause fetal harm when administered to a pregnant woman. Advise patients of the potential risk to a fetus. Advise females of reproductive potential to use effective contraception during treatment with TIVDAK and for 2 months after the last dose. Advise male patients with female partners of reproductive potential to use effective contraception during treatment with TIVDAK and for 4 months after the last dose.

    Adverse Reactions

    Across clinical trials of TIVDAK in 425 patients with r/mCC, the most common (≥25%) adverse reactions, including laboratory abnormalities, were hemoglobin decreased (45%), PN (39%), conjunctival adverse reactions (38%), nausea (37%), fatigue (36%), aspartate aminotransferase increased (33%), epistaxis (33%), alopecia (31%), alanine aminotransferase increased (30%), and hemorrhage (28%).

    innovaTV 301 Study: 250 patients with r/mCC with disease progression on or after systemic therapy

    Serious adverse reactions occurred in 33% of patients receiving TIVDAK; the most common (≥2%) were urinary tract infection (4.8%), small intestinal obstruction (2.4%), sepsis, abdominal pain, and hemorrhage (each 2%). Fatal adverse reactions occurred in 1.6% of patients who received TIVDAK, including acute kidney injury, pneumonia, sepsis, and SJS (each 0.4%).

    Adverse reactions leading to permanent discontinuation occurred in 15% of patients receiving TIVDAK; the most common (≥3%) were PN and ocular adverse reactions (each 6%). Adverse reactions leading to dose interruption occurred in 39% of patients receiving TIVDAK; the most common (≥3%) were ocular adverse reactions (16%) and PN (6%). Adverse reactions leading to dose reduction occurred in 30% of patients receiving TIVDAK; the most common (≥3%) were PN and ocular adverse reactions (each 10%). The ocular adverse reactions included conjunctival disorders (4.8%), keratopathy (4%), and dry eye (0.8%).

    innovaTV 204 Study: 101 patients with r/mCC with disease progression on or after chemotherapy

    Serious adverse reactions occurred in 43% of patients; the most common (≥3%) were ileus (6%), hemorrhage (5%), pneumonia (4%), PN, sepsis, constipation, and pyrexia (each 3%). Fatal adverse reactions occurred in 4% of patients who received TIVDAK, including septic shock, pneumonitis, sudden death, and multisystem organ failure (each 1%).

    Adverse reactions leading to permanent discontinuation occurred in 13% of patients receiving TIVDAK; the most common (≥3%) were PN (5%) and corneal adverse reactions (4%). Adverse reactions leading to dose interruption occurred in 47% of patients; the most common (≥3%) were PN (8%), conjunctival adverse reactions, and hemorrhage (each 4%). Adverse reactions leading to dose reduction occurred in 23% of patients; the most common (≥3%) were conjunctival adverse reactions (9%) and corneal adverse reactions (8%).

    Drug Interactions

    Strong CYP3A4 inhibitors: Concomitant use with strong CYP3A4 inhibitors may increase unconjugated monomethyl auristatin E (MMAE) exposure, which may increase the risk of TIVDAK adverse reactions. Closely monitor patients for TIVDAK adverse reactions.

    Use in Specific Populations

    Moderate or severe hepatic impairment: MMAE exposure and adverse reactions are increased. Avoid use.

    Lactation: Advise lactating women not to breastfeed during TIVDAK treatment and for at least 3 weeks after the last dose.

    INDICATION

    TIVDAK is indicated for the treatment of adult patients with recurrent or metastatic cervical cancer (r/mCC) with disease progression on or after chemotherapy.

    Please see full Prescribing Information, including BOXED WARNING for TIVDAK, linked on this site.

When to Consider Tivdak

  • Dr. Chase:

    Hello, I’m Dr. Dana Chase. Today I’ll be reviewing the patient profile of Tivdak (tisotumab vedotin-tftv), an antibody-drug conjugate for the treatment of adult patients with recurrent or metastatic cervical cancer with disease progression on or after chemotherapy.

    Please stay tuned for full Important Safety Information at the end of this video, and see the full Prescribing Information linked on this site. Let’s get started.

    VOICE OVER:

    TIVDAK is indicated for the treatment of adult patients with recurrent or metastatic cervical cancer (r/mCC) with disease progression on or after chemotherapy.

    SELECT IMPORTANT SAFETY INFORMATION

    BOXED WARNING: OCULAR TOXICITY

    TIVDAK can cause severe ocular toxicities resulting in changes in vision, including severe vision loss, and corneal ulceration. Conduct an ophthalmic exam, including an assessment of ocular symptoms, visual acuity, and slit lamp exam of the anterior segment of the eye prior to initiation of TIVDAK, prior to every cycle for the first nine cycles, and as clinically indicated. Adhere to the required premedication and eye care before, during, and after infusion. Withhold TIVDAK until improvement and resume, reduce the dose, or permanently discontinue, based on severity.

    Please stay tuned for full Important Safety Information at the end of this video and see the full Prescribing Information, including BOXED WARNING, linked on this site or at tivdakHCP.com.

    Dr. Chase:

    Before we talk about Tivdak, let’s discuss some of the unmet needs in cervical cancer. Cervical cancer continues to be a devastating disease.

    In the United States, it’s estimated that approximately 14,000 people will be diagnosed with cervical cancer and approximately 4,300 people will die from it in 2024. When considering diagnosis, it’s important to note that clinicians do not see these types of patients very often. In fact, 15% of cervical cancers are diagnosed at the metastatic stage. The 5-year survival rate is just 19% for patients with de novo metastatic disease. For those with recurrent disease, the 5-year survival rate is less than 5%. Historically, patients who were diagnosed with recurrent or metastatic cervical cancer were told that they had limited treatment options. The emergence of options in the second line over the past several years has opened up the dialogue for clinicians and for patients.

    Now, let’s talk about Tivdak and when clinicians should consider this therapy.

    To start, Tivdak is indicated for the treatment of adult patients with recurrent or metastatic cervical cancer with disease progression on or after chemotherapy. I consider Tivdak after my patients progress on first-line systemic therapy with a chemotherapy doublet plus targeted therapy, when appropriate. Though Tivdak is a Tissue Factor directed therapy, I would also like to point out that Tivdak does not require testing for a specific biomarker, which means one less test result to wait on before starting treatment.

    These days we rely a lot on biomarkers to tell us what therapies to put a patient on. This can be a really good thing for a patient if she has the biomarker, if the patient has the biomarker, but it can also be disappointing to the patient if the patient does not have the biomarker. So it’s always nice to have a treatment that doesn’t rely on a biomarker in terms of eligibility for treatment.

    Furthermore, the National Comprehensive Cancer Network (NCCN) recommends tisotumab vedotin-tftv or Tivdak as an NCCN Category 1 Preferred option for second-line or subsequent therapy for recurrent or metastatic cervical cancer.

    As a provider who understands the poor prognosis of advanced cervical cancer, I appreciate Tivdak because it allows me to continue discussions with patients about the next steps in their treatment journeys. I’d like to thank those of you who joined me today and encourage you to stay tuned for the full Important Safety Information.

    VOICE OVER:

    Important Safety Information

    BOXED WARNING: OCULAR TOXICITY

    TIVDAK can cause severe ocular toxicities resulting in changes in vision, including severe vision loss, and corneal ulceration. Conduct an ophthalmic exam, including an assessment of ocular symptoms, visual acuity, and slit lamp exam of the anterior segment of the eye prior to initiation of TIVDAK, prior to every cycle for the first nine cycles, and as clinically indicated. Adhere to the required premedication and eye care before, during, and after infusion. Withhold TIVDAK until improvement and resume, reduce the dose, or permanently discontinue, based on severity.

    Warnings and Precautions

    Ocular adverse reactions: TIVDAK can cause severe ocular adverse reactions, including conjunctivitis, keratopathy (keratitis, punctate keratitis, and ulcerative keratitis), and dry eye (increased lacrimation, eye pain, eye discharge, pruritus, irritation, and foreign body sensation), that may lead to changes in vision and/or corneal ulceration.

    Ocular adverse reactions occurred in 55% of patients with cervical cancer treated with TIVDAK across clinical trials. The most common were conjunctivitis (32%), dry eye (24%), keratopathy (17%), and blepharitis (5%). Grade 3 ocular adverse reactions occurred in 3.3% of patients, including severe ulcerative keratitis in 1.2% of patients. Nine patients (2.1%) experienced ulcerative keratitis (including one with perforation requiring corneal transplantation), six (1.4%) conjunctival ulcer, four (0.9%) corneal erosion, two (0.5%) conjunctival erosion, and two (0.5%) symblepharon.

    In innovaTV 301, 8 patients (3.2%) experienced delayed ocular adverse reactions occurring more than 30 days after discontinuation of TIVDAK. These adverse reactions included 3 patients with ulcerative keratitis, and one patient (each) with keratitis, punctate keratitis and corneal erosion, blepharitis and conjunctival hyperemia, conjunctival scar, and conjunctivitis and xerophthalmia.

    Refer patients to an eye care provider to conduct an ophthalmic exam prior to initiation of TIVDAK, prior to every cycle for the first nine cycles, and as clinically indicated. The exam should include visual acuity, slit lamp exam of the anterior segment of the eye, and an assessment of normal eye movement and ocular signs or symptoms which include dry or irritated eyes, eye secretions, or blurry vision.

    Adhere to the required premedication and eye care before, during, and after infusion to reduce the risk of ocular adverse reactions. Monitor for ocular toxicity and promptly refer patients to an eye care provider for any new or worsening ocular signs and symptoms. Withhold, reduce, or permanently discontinue TIVDAK based on the severity or persistence of the ocular adverse reaction.

    Peripheral neuropathy (PN) occurred in 39% of cervical cancer patients treated with TIVDAK across clinical trials; 6% of patients experienced Grade 3 PN. PN adverse reactions included peripheral sensory neuropathy (23%), PN (5%), paresthesia (3.8%), peripheral sensorimotor neuropathy (3.3%), muscular weakness (2.8%), and peripheral motor neuropathy (2.4%). One patient with another tumor type treated with TIVDAK at the recommended dose developed Guillain-Barre syndrome.

    Monitor patients for signs and symptoms of neuropathy such as paresthesia, tingling or a burning sensation, neuropathic pain, muscle weakness, or dysesthesia. For new or worsening PN, withhold, then dose reduce, or permanently discontinue TIVDAK based on the severity of PN.

    Hemorrhage occurred in 51% of cervical cancer patients treated with TIVDAK across clinical trials. The most common all grade hemorrhage adverse reaction was epistaxis (33%). Grade 3 hemorrhage occurred in 4% of patients.

    Monitor patients for signs and symptoms of hemorrhage. For patients experiencing pulmonary or central nervous system hemorrhage, permanently discontinue TIVDAK. For Grade ≥2 hemorrhage in any other location, withhold until bleeding has resolved, blood hemoglobin is stable, there is no bleeding diathesis that could increase the risk of continuing therapy, and there is no anatomical or pathologic condition that can increase the risk of hemorrhage recurrence. After resolution, either resume treatment or permanently discontinue TIVDAK.

    Pneumonitis that is severe, life-threatening, or fatal can occur in patients treated with antibody-drug conjugates containing vedotin, including TIVDAK. Among cervical cancer patients treated with TIVDAK across clinical trials, 4 patients (0.9%) experienced pneumonitis, including 1 patient who had a fatal outcome.

    Monitor patients for pulmonary symptoms of pneumonitis. Symptoms may include hypoxia, cough, dyspnea or interstitial infiltrates on radiologic exams. Infectious, neoplastic, and other causes for such symptoms should be excluded through appropriate investigations. Withhold TIVDAK for patients who develop persistent or recurrent Grade 2 pneumonitis and consider dose reduction. Permanently discontinue TIVDAK in all patients with Grade 3 or 4 pneumonitis.

    Severe cutaneous adverse reactions (SCAR), including events of fatal or life-threatening Stevens-Johnson syndrome (SJS), can occur in patients treated with TIVDAK. SCAR occurred in 1.6% of cervical cancer patients treated with TIVDAK across clinical trials. Grade ≥3 SCAR occurred in 0.5% of patients, including 1 patient who had a fatal outcome.

    Monitor patients for signs or symptoms of SCAR, which include target lesions, worsening skin reactions, blistering or peeling of the skin, painful sores in mouth, nose, throat, or genital area, fever or flu-like symptoms, and swollen lymph nodes. If signs or symptoms of SCAR occur, withhold TIVDAK until the etiology of the reaction has been determined. Early consultation with a specialist is recommended to ensure greater diagnostic accuracy and appropriate management. Permanently discontinue TIVDAK for confirmed Grade 3 or 4 SCAR, including SJS.

    Embryo-fetal toxicity: TIVDAK can cause fetal harm when administered to a pregnant woman. Advise patients of the potential risk to a fetus. Advise females of reproductive potential to use effective contraception during treatment with TIVDAK and for 2 months after the last dose. Advise male patients with female partners of reproductive potential to use effective contraception during treatment with TIVDAK and for 4 months after the last dose.

    Adverse Reactions

    Across clinical trials of TIVDAK in 425 patients with r/mCC, the most common (≥25%) adverse reactions, including laboratory abnormalities, were hemoglobin decreased (45%), PN (39%), conjunctival adverse reactions (38%), nausea (37%), fatigue (36%), aspartate aminotransferase increased (33%), epistaxis (33%), alopecia (31%), alanine aminotransferase increased (30%), and hemorrhage (28%).

    innovaTV 301 Study: 250 patients with r/mCC with disease progression on or after systemic therapy

    Serious adverse reactions occurred in 33% of patients receiving TIVDAK; the most common (≥2%) were urinary tract infection (4.8%), small intestinal obstruction (2.4%), sepsis, abdominal pain, and hemorrhage (each 2%). Fatal adverse reactions occurred in 1.6% of patients who received TIVDAK, including acute kidney injury, pneumonia, sepsis, and SJS (each 0.4%).

    Adverse reactions leading to permanent discontinuation occurred in 15% of patients receiving TIVDAK; the most common (≥3%) were PN and ocular adverse reactions (each 6%). Adverse reactions leading to dose interruption occurred in 39% of patients receiving TIVDAK; the most common (≥3%) were ocular adverse reactions (16%) and PN (6%). Adverse reactions leading to dose reduction occurred in 30% of patients receiving TIVDAK; the most common (≥3%) were PN and ocular adverse reactions (each 10%). The ocular adverse reactions included conjunctival disorders (4.8%), keratopathy (4%), and dry eye (0.8%).

    innovaTV 204 Study: 101 patients with r/mCC with disease progression on or after chemotherapy

    Serious adverse reactions occurred in 43% of patients; the most common (≥3%) were ileus (6%), hemorrhage (5%), pneumonia (4%), PN, sepsis, constipation, and pyrexia (each 3%). Fatal adverse reactions occurred in 4% of patients who received TIVDAK, including septic shock, pneumonitis, sudden death, and multisystem organ failure (each 1%).

    Adverse reactions leading to permanent discontinuation occurred in 13% of patients receiving TIVDAK; the most common (≥3%) were PN (5%) and corneal adverse reactions (4%). Adverse reactions leading to dose interruption occurred in 47% of patients; the most common (≥3%) were PN (8%), conjunctival adverse reactions, and hemorrhage (each 4%). Adverse reactions leading to dose reduction occurred in 23% of patients; the most common (≥3%) were conjunctival adverse reactions (9%) and corneal adverse reactions (8%).

    Drug Interactions

    Strong CYP3A4 inhibitors: Concomitant use with strong CYP3A4 inhibitors may increase unconjugated monomethyl auristatin E (MMAE) exposure, which may increase the risk of TIVDAK adverse reactions. Closely monitor patients for TIVDAK adverse reactions.

    Use in Specific Populations

    Moderate or severe hepatic impairment: MMAE exposure and adverse reactions are increased. Avoid use.

    Lactation: Advise lactating women not to breastfeed during TIVDAK treatment and for at least 3 weeks after the last dose.

    INDICATION

    TIVDAK is indicated for the treatment of adult patients with recurrent or metastatic cervical cancer (r/mCC) with disease progression on or after chemotherapy.

    Please see full Prescribing Information, including BOXED WARNING for TIVDAK, linked on this site.

PEERspectives: Effective Care Coordination

  • Dr. Krivak:

    Cervical cancer is a complex disease, and it takes a whole team working closely together to treat patients. I’m joined today by Courtney Arn, a Nurse Practitioner with over 11 years in OB/GYN oncology, and we will talk about some of our experiences in offering patient-first care.

    I’m Dr. Thomas Krivak, a gynecologic oncologist, and this is Tivdak Peerspectives.

    VOICE OVER:

    INDICATION

    TIVDAK (tistomab vedotin tftv) is indicated for the treatment of adult patients with recurrent or metastatic cervical cancer (r/mCC) with disease progression on or after chemotherapy.

    BOXED WARNING: OCULAR TOXICITY

    TIVDAK can cause severe ocular toxicities resulting in changes in vision, including severe vision loss, and corneal ulceration. Conduct an ophthalmic exam, including an assessment of ocular symptoms, visual acuity, and slit lamp exam of the anterior segment of the eye prior to initiation of TIVDAK, prior to every cycle for the first nine cycles, and as clinically indicated. Adhere to the required premedication and eye care before, during, and after infusion. Withhold TIVDAK until improvement and resume, reduce the dose, or permanently discontinue, based on severity.

    Please stay tuned for Important Safety Information later in this video and see the full Prescribing Information, including BOXED WARNING, and Medication Guide for TIVDAK, linked on this site or at tivdakHCP.com.

    Dr. Krivak:

    Courtney, thank you for joining us today. I’ve heard you have a lot of experience with Tivdak, is that correct?

    Courtney Arn:

    Yes, I work at an academic center, and our clinical team participated in the Tivdak clinical trials and have been using Tivdak since its FDA approval in 2021. So my team and I have coordinated care for a lot of Tivdak patients.

    Dr. Krivak:

    Let’s talk about that. Care teams often involve many different healthcare providers with unique roles each communicating at different points with patients.

    One thing we do in our practice, and I’m curious if you do the same, is we make a point that the patients meet everyone on their care team, so they’re familiar with them.

    Patients often feel overwhelmed, so explaining who we all are and why we’re involved, can really help.

    Courtney Arn:

    Definitely. We do make it a point to meet all of our patients at that initial visit.

    Some institutions even have handouts that show roles, names, and pictures of each member of the team.

    It’s important that the patients know who to call if they have questions. Or that, when someone calls them, it’s someone they know is part of their personal team.

    Dr. Krivak:

    It helps patients to know we’re all here for them—but when you have so many different people involved in treatment at different points, there’s risk of things falling through the cracks, or patients getting conflicting guidance. How do you manage this in your team?

    Courtney Arn:

    Yeah, so, one thing that I think really helps is that all of our patients have a primary nurse practitioner or PA who helps coordinate their care throughout treatment. But, like you said, we each talk to the patients at different points.

    So, for example, our patients often see their infusion nurses after they’ve seen the APP and/or oncologist, and sometimes they think of new questions or symptoms they forgot to mention.

    This is why it’s so important that we make sure our whole team is on the same page that anyone is empowered to answer questions and that we’re regularly communicating with the rest of the team, to ensure we’re offering clear, consistent information to our patients.

    Dr. Krivak:

    In my own practice, we share patient information through the chart and make sure to check with one another.

    We also have regular in-clinic patient reviews with the team, where everyone will sit down and catch up on how our patients are doing; how was this patient’s first cycle? Are they having any side effects? Should we make any changes to their treatment plan? I find that more communication is better than less.

    Is there anything else you do in your practice to ensure nothing falls through the cracks?

    Courtney Arn:

    Yeah, I agree. We do similar things.

    One other thing we do is make use of “smart phrases”—which is essentially, a checklist of what to ask our patients.

    So, when a nurse checks a patient in, for example, we have a list of phrases, such as “are you having any of these symptoms…” or, specifically for Tivdak, “do you have your eye drops with you?”

    We use the standard toxicity assessment, but this smart phrase checklist ensures that we do one final check to make sure that it’s appropriate to continue treatment that day.

    Dr. Krivak:

    You mentioned patient’s eye drops. I remember when Tivdak was first approved, I was anxious about the risk of severe ocular adverse reactions, because eye care is outside my realm of expertise.

    Even though I had some experience working with eye care providers for other cancer treatments, we still had to work through some of our nervousness with our first Tivdak patients.

    Courtney Arn:

    I think that’s a common feeling for people who are treating with Tivdak for the first time.

    Courtney Arn:

    The thing to realize is, we don’t need to become eye experts: we need to make sure that the patient has seen an eye care provider, had the appropriate exams as per the Tivdak prescribing information, and that their assessment has been completed.

    We check the ocular assessment form against the dose modification chart—which we have printed for easy reference in our office—and see whether the dose needs to be modified, withheld, discontinued, or if the patient is okay to receive Tivdak at their full dose.

    In this way, the patient’s eye care provider becomes another member of our team by helping us monitor and manage ocular adverse reactions.

    My advice is to align, as a care team, who is responsible for making sure the patient has completed the Required Eye Care prior to their infusion day.

    Dr. Krivak:

    Thank you, Courtney. And thank you for the crucial role you play in patient’s lives.

    Courtney Arn:

    It’s my pleasure. Thank you as well.

    Dr. Krivak:

    And, if you’re curious to learn more about the eye care associated with Tivdak, watch Episode 2 of our Peerspective series, in which I will be interviewing Dr. Campbell, an eye care specialist, about her experiences with Tivdak.

    Dr. Krivak:

    Please stay tuned for important safety information about Tivdak.

    VOICE OVER:

    Important Safety Information

    BOXED WARNING: OCULAR TOXICITY

    TIVDAK can cause severe ocular toxicities resulting in changes in vision, including severe vision loss, and corneal ulceration. Conduct an ophthalmic exam, including an assessment of ocular symptoms, visual acuity, and slit lamp exam of the anterior segment of the eye prior to initiation of TIVDAK, prior to every cycle for the first nine cycles, and as clinically indicated. Adhere to the required premedication and eye care before, during, and after infusion. Withhold TIVDAK until improvement and resume, reduce the dose, or permanently discontinue, based on severity.

    Warnings and Precautions

    Ocular adverse reactions: TIVDAK can cause severe ocular adverse reactions, including conjunctivitis, keratopathy (keratitis, punctate keratitis, and ulcerative keratitis), and dry eye (increased lacrimation, eye pain, eye discharge, pruritus, irritation, and foreign body sensation), that may lead to changes in vision and/or corneal ulceration.

    Ocular adverse reactions occurred in 55% of patients with cervical cancer treated with TIVDAK across clinical trials. The most common were conjunctivitis (32%), dry eye (24%), keratopathy (17%), and blepharitis (5%). Grade 3 ocular adverse reactions occurred in 3.3% of patients, including severe ulcerative keratitis in 1.2% of patients. Nine patients (2.1%) experienced ulcerative keratitis (including one with perforation requiring corneal transplantation), six (1.4%) conjunctival ulcer, four (0.9%) corneal erosion, two (0.5%) conjunctival erosion, and two (0.5%) symblepharon.

    In innovaTV 301, 8 patients (3.2%) experienced delayed ocular adverse reactions occurring more than 30 days after discontinuation of TIVDAK. These adverse reactions included 3 patients with ulcerative keratitis, and one patient (each) with keratitis, punctate keratitis and corneal erosion, blepharitis and conjunctival hyperemia, conjunctival scar, and conjunctivitis and xerophthalmia.

    Refer patients to an eye care provider to conduct an ophthalmic exam prior to initiation of TIVDAK, prior to every cycle for the first nine cycles, and as clinically indicated. The exam should include visual acuity, slit lamp exam of the anterior segment of the eye, and an assessment of normal eye movement and ocular signs or symptoms which include dry or irritated eyes, eye secretions, or blurry vision.

    Adhere to the required premedication and eye care before, during, and after infusion to reduce the risk of ocular adverse reactions. Monitor for ocular toxicity and promptly refer patients to an eye care provider for any new or worsening ocular signs and symptoms. Withhold, reduce, or permanently discontinue TIVDAK based on the severity or persistence of the ocular adverse reaction.

    Peripheral neuropathy (PN) occurred in 39% of cervical cancer patients treated with TIVDAK across clinical trials; 6% of patients experienced Grade 3 PN. PN adverse reactions included peripheral sensory neuropathy (23%), PN (5%), paresthesia (3.8%), peripheral sensorimotor neuropathy (3.3%), muscular weakness (2.8%), and peripheral motor neuropathy (2.4%). One patient with another tumor type treated with TIVDAK at the recommended dose developed Guillain-Barre syndrome.
    Monitor patients for signs and symptoms of neuropathy such as paresthesia, tingling or a burning sensation, neuropathic pain, muscle weakness, or dysesthesia. For new or worsening PN, withhold, then dose reduce, or permanently discontinue TIVDAK based on the severity of PN.

    Hemorrhage occurred in 51% of cervical cancer patients treated with TIVDAK across clinical trials. The most common all grade hemorrhage adverse reaction was epistaxis (33%). Grade 3 hemorrhage occurred in 4% of patients.

    Monitor patients for signs and symptoms of hemorrhage. For patients experiencing pulmonary or central nervous system hemorrhage, permanently discontinue TIVDAK. For Grade ≥2 hemorrhage in any other location, withhold until bleeding has resolved, blood hemoglobin is stable, there is no bleeding diathesis that could increase the risk of continuing therapy, and there is no anatomical or pathologic condition that can increase the risk of hemorrhage recurrence. After resolution, either resume treatment or permanently discontinue TIVDAK.

    Pneumonitis that is severe, life-threatening, or fatal can occur in patients treated with antibody-drug conjugates containing vedotin, including TIVDAK. Among cervical cancer patients treated with TIVDAK across clinical trials, 4 patients (0.9%) experienced pneumonitis, including 1 patient who had a fatal outcome.

    Monitor patients for pulmonary symptoms of pneumonitis. Symptoms may include hypoxia, cough, dyspnea or interstitial infiltrates on radiologic exams. Infectious, neoplastic, and other causes for such symptoms should be excluded through appropriate investigations. Withhold TIVDAK for patients who develop persistent or recurrent Grade 2 pneumonitis and consider dose reduction. Permanently discontinue TIVDAK in all patients with Grade 3 or 4 pneumonitis.

    Severe cutaneous adverse reactions (SCAR), including events of fatal or life-threatening Stevens-Johnson syndrome (SJS), can occur in patients treated with TIVDAK. SCAR occurred in 1.6% of cervical cancer patients treated with TIVDAK across clinical trials. Grade ≥3 SCAR occurred in 0.5% of patients, including 1 patient who had a fatal outcome.

    Monitor patients for signs or symptoms of SCAR, which include target lesions, worsening skin reactions, blistering or peeling of the skin, painful sores in mouth, nose, throat, or genital area, fever or flu-like symptoms, and swollen lymph nodes. If signs or symptoms of SCAR occur, withhold TIVDAK until the etiology of the reaction has been determined. Early consultation with a specialist is recommended to ensure greater diagnostic accuracy and appropriate management. Permanently discontinue TIVDAK for confirmed Grade 3 or 4 SCAR, including SJS.

    Embryo-fetal toxicity: TIVDAK can cause fetal harm when administered to a pregnant woman. Advise patients of the potential risk to a fetus. Advise females of reproductive potential to use effective contraception during treatment with TIVDAK and for 2 months after the last dose. Advise male patients with female partners of reproductive potential to use effective contraception during treatment with TIVDAK and for 4 months after the last dose.

    Adverse Reactions

    Across clinical trials of TIVDAK in 425 patients with r/mCC, the most common (≥25%) adverse reactions, including laboratory abnormalities, were hemoglobin decreased (45%), PN (39%), conjunctival adverse reactions (38%), nausea (37%), fatigue (36%), aspartate aminotransferase increased (33%), epistaxis (33%), alopecia (31%), alanine aminotransferase increased (30%), and hemorrhage (28%).

    innovaTV 301 Study: 250 patients with r/mCC with disease progression on or after systemic therapy

    Serious adverse reactions occurred in 33% of patients receiving TIVDAK; the most common (≥2%) were urinary tract infection (4.8%), small intestinal obstruction (2.4%), sepsis, abdominal pain, and hemorrhage (each 2%). Fatal adverse reactions occurred in 1.6% of patients who received TIVDAK, including acute kidney injury, pneumonia, sepsis, and SJS (each 0.4%).

    Adverse reactions leading to permanent discontinuation occurred in 15% of patients receiving TIVDAK; the most common (≥3%) were PN and ocular adverse reactions (each 6%). Adverse reactions leading to dose interruption occurred in 39% of patients receiving TIVDAK; the most common (≥3%) were ocular adverse reactions (16%) and PN (6%). Adverse reactions leading to dose reduction occurred in 30% of patients receiving TIVDAK; the most common (≥3%) were PN and ocular adverse reactions (each 10%). The ocular adverse reactions included conjunctival disorders (4.8%), keratopathy (4%), and dry eye (0.8%).

    innovaTV 204 Study: 101 patients with r/mCC with disease progression on or after chemotherapy

    Serious adverse reactions occurred in 43% of patients; the most common (≥3%) were ileus (6%), hemorrhage (5%), pneumonia (4%), PN, sepsis, constipation, and pyrexia (each 3%). Fatal adverse reactions occurred in 4% of patients who received TIVDAK, including septic shock, pneumonitis, sudden death, and multisystem organ failure (each 1%).

    Adverse reactions leading to permanent discontinuation occurred in 13% of patients receiving TIVDAK; the most common (≥3%) were PN (5%) and corneal adverse reactions (4%). Adverse reactions leading to dose interruption occurred in 47% of patients; the most common (≥3%) were PN (8%), conjunctival adverse reactions, and hemorrhage (each 4%). Adverse reactions leading to dose reduction occurred in 23% of patients; the most common (≥3%) were conjunctival adverse reactions (9%) and corneal adverse reactions (8%).

    Drug Interactions

    Strong CYP3A4 inhibitors: Concomitant use with strong CYP3A4 inhibitors may increase unconjugated monomethyl auristatin E (MMAE) exposure, which may increase the risk of TIVDAK adverse reactions. Closely monitor patients for TIVDAK adverse reactions.

    Use in Specific Populations

    Moderate or severe hepatic impairment: MMAE exposure and adverse reactions are increased. Avoid use.

    Lactation: Advise lactating women not to breastfeed during TIVDAK treatment and for at least 3 weeks after the last dose.

    INDICATION

    TIVDAK is indicated for the treatment of adult patients with recurrent or metastatic cervical cancer (r/mCC) with disease progression on or after chemotherapy.

    Please see full Prescribing Information, including BOXED WARNING for TIVDAK, at tivdakHCP.com.

PEERspectives: An Eye on Tivdak

  • Dr. Krivak:

    As more treatment options for advanced cervical cancer have become available, we’ve learned to adapt to their different protocols, and find ourselves collaborating more and more with specialists from other fields.

    I’m here today with Dr. Kayla Campbell, an optometrist, and we will talk about ocular adverse reactions in oncology.

    I’m Dr. Thomas Krivak, a gynecologic oncologist, and this is Tivdak Peerspectives.

    VOICE OVER:

    INDICATION

    TIVDAK (tisotumab vedotin tftv) is indicated for the treatment of adult patients with recurrent or metastatic cervical cancer (r/mCC) with disease progression on or after chemotherapy.

    BOXED WARNING: OCULAR TOXICITY

    TIVDAK can cause severe ocular toxicities resulting in changes in vision, including severe vision loss, and corneal ulceration. Conduct an ophthalmic exam, including an assessment of ocular symptoms, visual acuity, and slit lamp exam of the anterior segment of the eye prior to initiation of TIVDAK, prior to every cycle for the first nine cycles, and as clinically indicated. Adhere to the required premedication and eye care before, during, and after infusion. Withhold TIVDAK until improvement and resume, reduce the dose, or permanently discontinue, based on severity.

    Please stay tuned for Important Safety Information later in this video and see the full Prescribing Information, including BOXED WARNING, and Medication Guide for TIVDAK, linked on this site or at tivdakHCP.com.

    Dr. Krivak:

    Dr. Campbell, thank you for joining us.

    Dr. Campbell:

    Thank you for having me.

    Dr. Krivak:

    Now, Tivdak is an oncology treatment. So how did you, as an eye care provider, become familiar with it?

    Dr. Campbell:

    At the time, I was practicing in rural West Virginia, where there were very few gyn oncologists.

    One day, one of the oncologists called me and asked if I could help with a drug’s required eye care.

    So I got the information about Tivdak, met with a sales rep. And at first, I was a little intimidated. But I spoke to some other eye care providers who helped me feel more confident.

    And after my first couple of patients I realized: my role in cervical cancer treatment isn’t that different from what I do every day. I’m an optometrist, and I manage ocular surface diseases. And that’s what we’re dealing with here.

    Dr. Krivak:

    So tell me more about that.

    I know that the Tivdak Required Eye Care may help reduce the risk of ocular adverse reactions, but exactly what does that entail?

    Dr. Campbell:

    Well, for the baseline visit, we’ll check vision, we’ll check eye movement, and we’ll do a slit lamp exam.

    Dr. Campbell:

    I’ll also set the patient up with their required premedication: so, a topical corticosteroid eye drop that they take three times daily, for three days, starting the day of their infusion; the topical vasoconstrictor drops, which they’ll take immediately prior to the infusion; and the lubricating eye drops, that they’ll take throughout and for 30 days after their Tivdak treatment.

    We will conduct ophthalmic exams before each cycle of the patient’s first 9 cycles of treatment and as clinically indicated, monitoring for and managing any of the ocular adverse reactions, and report our exam findings to the patient’s oncologist.

    Dr. Krivak:

    That’s right. And before the patient’s infusion appointment, my team will review your completed ocular assessment form against the dose modification chart to see if they need a delay or discontinue, reduce the dose, or if we can proceed as normal.

    Dr. Campbell:

    Exactly. I didn’t need to become an expert in oncology, just as you didn’t need to become an expert in eye care.

    It’s just about doing what we do every day, and sharing our expertise with one another.

    Dr. Krivak:

    So how is Tivdak required eye care different from what you typically do as an optometrist?

    Dr. Campbell:

    In some ways, it’s very similar. I do ophthalmic exams and prescribe eye drops. Many of the potential adverse reactions for Tivdak are eye conditions that I was already used to treating and managing. And I often send reports to other specialists.

    So it’s not about what I’m doing, but more of why. So, before Tivdak, there hadn’t been many times in my career that I’d have been able to help with something like cancer care.

    So, to be part of a patient’s Tivdak team feels really meaningful.

    Dr. Krivak:

    Given your experience with Tivdak, it sounds like you became the go-to optometrist for your nearby oncologist.

    In my more urban practice, my patients often already have optometrists or ophthalmologists. I typically work with them, so patients can stay with someone that they know and trust.

    What do you think the pros and cons are between keeping patients with their familiar eye care provider, or finding someone who may be new to the patient but have more experience with Tivdak?

    Dr. Campbell:

    Yeah, so, I think that there are benefits to both. I’ve met oncologists like yourself, that have had plenty of success keeping patients with their personal eye care providers—either ophthalmologists or optometrists.

    Still, I feel like there are benefits to having a relationship with an eye care provider that you know and trust.

    When I started seeing more Tivdak patients, the local oncologist could reach out to me with any direct questions, and I could contact him if the patient mentioned anything to me that I thought he should know.

    And I was able to take on the role of educating the patients, helping them to feel more comfortable about what we’re doing and how to watch for toxicity, and how we’ll help manage those side effects, if they occur.

    Dr. Krivak:

    So, if I wanted to find an eye care provider to partner with consistently, do you have any advice on how I should establish that relationship?

    Dr. Campbell:

    Yeah, so, I mean, I would try to find someone who really understands the importance of what we’re doing and is willing to give patients the time and flexibility that they deserve.

    I would reach out to the eye care provider rather than just sending a patient referral. These appointments are incredibly time-sensitive and important for the patient’s Tivdak treatment. So, I will make time for them, no matter what else is going on that day.

    Dr. Krivak:

    Thank you, Dr. Campbell. I really appreciate you’ve offered a great perspective today and all the extra effort you do for caring for these patients.

    Dr. Campbell:

    Yeah, thank you, as well, for the work that you do.

    Dr. Krivak:

    And if you have any questions about Tivdak, you can reach out to your representative.
    You can request a rep at tivdakHCP.com.

    Please stay tuned for important safety information about Tivdak.

    VOICE OVER:

    Important Safety Information

    BOXED WARNING: OCULAR TOXICITY

    TIVDAK can cause severe ocular toxicities resulting in changes in vision, including severe vision loss, and corneal ulceration. Conduct an ophthalmic exam, including an assessment of ocular symptoms, visual acuity, and slit lamp exam of the anterior segment of the eye prior to initiation of TIVDAK, prior to every cycle for the first nine cycles, and as clinically indicated. Adhere to the required premedication and eye care before, during, and after infusion. Withhold TIVDAK until improvement and resume, reduce the dose, or permanently discontinue, based on severity.

    Warnings and Precautions

    Ocular adverse reactions: TIVDAK can cause severe ocular adverse reactions, including conjunctivitis, keratopathy (keratitis, punctate keratitis, and ulcerative keratitis), and dry eye (increased lacrimation, eye pain, eye discharge, pruritus, irritation, and foreign body sensation), that may lead to changes in vision and/or corneal ulceration.

    Ocular adverse reactions occurred in 55% of patients with cervical cancer treated with TIVDAK across clinical trials. The most common were conjunctivitis (32%), dry eye (24%), keratopathy (17%), and blepharitis (5%). Grade 3 ocular adverse reactions occurred in 3.3% of patients, including severe ulcerative keratitis in 1.2% of patients. Nine patients (2.1%) experienced ulcerative keratitis (including one with perforation requiring corneal transplantation), six (1.4%) conjunctival ulcer, four (0.9%) corneal erosion, two (0.5%) conjunctival erosion, and two (0.5%) symblepharon.

    In innovaTV 301, 8 patients (3.2%) experienced delayed ocular adverse reactions occurring more than 30 days after discontinuation of TIVDAK. These adverse reactions included 3 patients with ulcerative keratitis, and one patient (each) with keratitis, punctate keratitis and corneal erosion, blepharitis and conjunctival hyperemia, conjunctival scar, and conjunctivitis and xerophthalmia.

    Refer patients to an eye care provider to conduct an ophthalmic exam prior to initiation of TIVDAK, prior to every cycle for the first nine cycles, and as clinically indicated. The exam should include visual acuity, slit lamp exam of the anterior segment of the eye, and an assessment of normal eye movement and ocular signs or symptoms which include dry or irritated eyes, eye secretions, or blurry vision.

    Adhere to the required premedication and eye care before, during, and after infusion to reduce the risk of ocular adverse reactions. Monitor for ocular toxicity and promptly refer patients to an eye care provider for any new or worsening ocular signs and symptoms. Withhold, reduce, or permanently discontinue TIVDAK based on the severity or persistence of the ocular adverse reaction.

    Peripheral neuropathy (PN) occurred in 39% of cervical cancer patients treated with TIVDAK across clinical trials; 6% of patients experienced Grade 3 PN. PN adverse reactions included peripheral sensory neuropathy (23%), PN (5%), paresthesia (3.8%), peripheral sensorimotor neuropathy (3.3%), muscular weakness (2.8%), and peripheral motor neuropathy (2.4%). One patient with another tumor type treated with TIVDAK at the recommended dose developed Guillain-Barre syndrome.
    Monitor patients for signs and symptoms of neuropathy such as paresthesia, tingling or a burning sensation, neuropathic pain, muscle weakness, or dysesthesia. For new or worsening PN, withhold, then dose reduce, or permanently discontinue TIVDAK based on the severity of PN.

    Hemorrhage occurred in 51% of cervical cancer patients treated with TIVDAK across clinical trials. The most common all grade hemorrhage adverse reaction was epistaxis (33%). Grade 3 hemorrhage occurred in 4% of patients.

    Monitor patients for signs and symptoms of hemorrhage. For patients experiencing pulmonary or central nervous system hemorrhage, permanently discontinue TIVDAK. For Grade ≥2 hemorrhage in any other location, withhold until bleeding has resolved, blood hemoglobin is stable, there is no bleeding diathesis that could increase the risk of continuing therapy, and there is no anatomical or pathologic condition that can increase the risk of hemorrhage recurrence. After resolution, either resume treatment or permanently discontinue TIVDAK.

    Pneumonitis that is severe, life-threatening, or fatal can occur in patients treated with antibody-drug conjugates containing vedotin, including TIVDAK. Among cervical cancer patients treated with TIVDAK across clinical trials, 4 patients (0.9%) experienced pneumonitis, including 1 patient who had a fatal outcome.

    Monitor patients for pulmonary symptoms of pneumonitis. Symptoms may include hypoxia, cough, dyspnea or interstitial infiltrates on radiologic exams. Infectious, neoplastic, and other causes for such symptoms should be excluded through appropriate investigations. Withhold TIVDAK for patients who develop persistent or recurrent Grade 2 pneumonitis and consider dose reduction. Permanently discontinue TIVDAK in all patients with Grade 3 or 4 pneumonitis.

    Severe cutaneous adverse reactions (SCAR), including events of fatal or life-threatening Stevens-Johnson syndrome (SJS), can occur in patients treated with TIVDAK. SCAR occurred in 1.6% of cervical cancer patients treated with TIVDAK across clinical trials. Grade ≥3 SCAR occurred in 0.5% of patients, including 1 patient who had a fatal outcome.

    Monitor patients for signs or symptoms of SCAR, which include target lesions, worsening skin reactions, blistering or peeling of the skin, painful sores in mouth, nose, throat, or genital area, fever or flu-like symptoms, and swollen lymph nodes. If signs or symptoms of SCAR occur, withhold TIVDAK until the etiology of the reaction has been determined. Early consultation with a specialist is recommended to ensure greater diagnostic accuracy and appropriate management. Permanently discontinue TIVDAK for confirmed Grade 3 or 4 SCAR, including SJS.

    Embryo-fetal toxicity: TIVDAK can cause fetal harm when administered to a pregnant woman. Advise patients of the potential risk to a fetus. Advise females of reproductive potential to use effective contraception during treatment with TIVDAK and for 2 months after the last dose. Advise male patients with female partners of reproductive potential to use effective contraception during treatment with TIVDAK and for 4 months after the last dose.

    Adverse Reactions

    Across clinical trials of TIVDAK in 425 patients with r/mCC, the most common (≥25%) adverse reactions, including laboratory abnormalities, were hemoglobin decreased (45%), PN (39%), conjunctival adverse reactions (38%), nausea (37%), fatigue (36%), aspartate aminotransferase increased (33%), epistaxis (33%), alopecia (31%), alanine aminotransferase increased (30%), and hemorrhage (28%).

    innovaTV 301 Study: 250 patients with r/mCC with disease progression on or after systemic therapy

    Serious adverse reactions occurred in 33% of patients receiving TIVDAK; the most common (≥2%) were urinary tract infection (4.8%), small intestinal obstruction (2.4%), sepsis, abdominal pain, and hemorrhage (each 2%). Fatal adverse reactions occurred in 1.6% of patients who received TIVDAK, including acute kidney injury, pneumonia, sepsis, and SJS (each 0.4%).

    Adverse reactions leading to permanent discontinuation occurred in 15% of patients receiving TIVDAK; the most common (≥3%) were PN and ocular adverse reactions (each 6%). Adverse reactions leading to dose interruption occurred in 39% of patients receiving TIVDAK; the most common (≥3%) were ocular adverse reactions (16%) and PN (6%). Adverse reactions leading to dose reduction occurred in 30% of patients receiving TIVDAK; the most common (≥3%) were PN and ocular adverse reactions (each 10%). The ocular adverse reactions included conjunctival disorders (4.8%), keratopathy (4%), and dry eye (0.8%).

    innovaTV 204 Study: 101 patients with r/mCC with disease progression on or after chemotherapy

    Serious adverse reactions occurred in 43% of patients; the most common (≥3%) were ileus (6%), hemorrhage (5%), pneumonia (4%), PN, sepsis, constipation, and pyrexia (each 3%). Fatal adverse reactions occurred in 4% of patients who received TIVDAK, including septic shock, pneumonitis, sudden death, and multisystem organ failure (each 1%).

    Adverse reactions leading to permanent discontinuation occurred in 13% of patients receiving TIVDAK; the most common (≥3%) were PN (5%) and corneal adverse reactions (4%). Adverse reactions leading to dose interruption occurred in 47% of patients; the most common (≥3%) were PN (8%), conjunctival adverse reactions, and hemorrhage (each 4%). Adverse reactions leading to dose reduction occurred in 23% of patients; the most common (≥3%) were conjunctival adverse reactions (9%) and corneal adverse reactions (8%).

    Drug Interactions

    Strong CYP3A4 inhibitors: Concomitant use with strong CYP3A4 inhibitors may increase unconjugated monomethyl auristatin E (MMAE) exposure, which may increase the risk of TIVDAK adverse reactions. Closely monitor patients for TIVDAK adverse reactions.

    Use in Specific Populations

    Moderate or severe hepatic impairment: MMAE exposure and adverse reactions are increased. Avoid use.

    Lactation: Advise lactating women not to breastfeed during TIVDAK treatment and for at least 3 weeks after the last dose.

    INDICATION

    TIVDAK is indicated for the treatment of adult patients with recurrent or metastatic cervical cancer (r/mCC) with disease progression on or after chemotherapy.

    Please see full Prescribing Information, including BOXED WARNING for TIVDAK, at tivdakHCP.com.

NCCN
Guidelines®
Update

Tisotumab vedotin-tftv (Tivdak) is the ONLY NCCN CATEGORY 1 PREFERRED option for second-line or subsequent therapy for recurrent or metastatic cervical cancer recommended by the National Comprehensive Cancer Network® (NCCN®).

Tisotumab vedotin-tftv (Tivdak) is the ONLY NCCN CATEGORY 1 PREFERRED option for second-line or subsequent therapy for recurrent or metastatic cervical cancer recommended by the NCCN.

See reference

Important Safety Information

BOXED WARNING: OCULAR TOXICITY

TIVDAK can cause severe ocular toxicities resulting in changes in vision, including severe vision loss, and corneal ulceration. Conduct an ophthalmic exam, including an assessment of ocular symptoms, visual acuity, and slit lamp exam of the anterior segment of the eye prior to initiation of TIVDAK, prior to every cycle for the first nine cycles, and as clinically indicated. Adhere to the required premedication and eye care before, during, and after infusion. Withhold TIVDAK until improvement and resume, reduce the dose, or permanently discontinue, based on severity.

Warnings and Precautions

Ocular adverse reactions: TIVDAK can cause severe ocular adverse reactions, including conjunctivitis, keratopathy (keratitis, punctate keratitis, and ulcerative keratitis), and dry eye (increased lacrimation, eye pain, eye discharge, pruritus, irritation, and foreign body sensation), that may lead to changes in vision and/or corneal ulceration.

Ocular adverse reactions occurred in 55% of patients with cervical cancer treated with TIVDAK across clinical trials. The most common were conjunctivitis (32%), dry eye (24%), keratopathy (17%), and blepharitis (5%). Grade 3 ocular adverse reactions occurred in 3.3% of patients, including severe ulcerative keratitis in 1.2% of patients. Nine patients (2.1%) experienced ulcerative keratitis (including one with perforation requiring corneal transplantation), six (1.4%) conjunctival ulcer, four (0.9%) corneal erosion, two (0.5%) conjunctival erosion, and two (0.5%) symblepharon.

In innovaTV 301, 8 patients (3.2%) experienced delayed ocular adverse reactions occurring more than 30 days after discontinuation of TIVDAK. These adverse reactions included 3 patients with ulcerative keratitis, and one patient (each) with keratitis, punctate keratitis and corneal erosion, blepharitis and conjunctival hyperemia, conjunctival scar, and conjunctivitis and xerophthalmia.

Refer patients to an eye care provider to conduct an ophthalmic exam prior to initiation of TIVDAK, prior to every cycle for the first nine cycles, and as clinically indicated. The exam should include visual acuity, slit lamp exam of the anterior segment of the eye, and an assessment of normal eye movement and ocular signs or symptoms which include dry or irritated eyes, eye secretions, or blurry vision.

Adhere to the required premedication and eye care before, during, and after infusion to reduce the risk of ocular adverse reactions. Monitor for ocular toxicity and promptly refer patients to an eye care provider for any new or worsening ocular signs and symptoms. Withhold, reduce, or permanently discontinue TIVDAK based on the severity or persistence of the ocular adverse reaction.

Peripheral neuropathy (PN) occurred in 39% of cervical cancer patients treated with TIVDAK across clinical trials; 6% of patients experienced Grade 3 PN. PN adverse reactions included peripheral sensory neuropathy (23%), PN (5%), paresthesia (3.8%), peripheral sensorimotor neuropathy (3.3%), muscular weakness (2.8%), and peripheral motor neuropathy (2.4%). One patient with another tumor type treated with TIVDAK at the recommended dose developed Guillain-Barre syndrome.

Monitor patients for signs and symptoms of neuropathy such as paresthesia, tingling or a burning sensation, neuropathic pain, muscle weakness, or dysesthesia. For new or worsening PN, withhold, then dose reduce, or permanently discontinue TIVDAK based on the severity of PN.

Hemorrhage occurred in 51% of cervical cancer patients treated with TIVDAK across clinical trials. The most common all grade hemorrhage adverse reaction was epistaxis (33%). Grade 3 hemorrhage occurred in 4% of patients.

Monitor patients for signs and symptoms of hemorrhage. For patients experiencing pulmonary or central nervous system hemorrhage, permanently discontinue TIVDAK. For Grade ≥2 hemorrhage in any other location, withhold until bleeding has resolved, blood hemoglobin is stable, there is no bleeding diathesis that could increase the risk of continuing therapy, and there is no anatomical or pathologic condition that can increase the risk of hemorrhage recurrence. After resolution, either resume treatment or permanently discontinue TIVDAK.

Pneumonitis that is severe, life-threatening, or fatal can occur in patients treated with antibody-drug conjugates containing vedotin, including TIVDAK. Among cervical cancer patients treated with TIVDAK across clinical trials, 4 patients (0.9%) experienced pneumonitis, including 1 patient who had a fatal outcome.

Monitor patients for pulmonary symptoms of pneumonitis. Symptoms may include hypoxia, cough, dyspnea or interstitial infiltrates on radiologic exams. Infectious, neoplastic, and other causes for such symptoms should be excluded through appropriate investigations. Withhold TIVDAK for patients who develop persistent or recurrent Grade 2 pneumonitis and consider dose reduction. Permanently discontinue TIVDAK in all patients with Grade 3 or 4 pneumonitis.

Severe cutaneous adverse reactions (SCAR), including events of fatal or life-threatening Stevens-Johnson syndrome (SJS), can occur in patients treated with TIVDAK. SCAR occurred in 1.6% of cervical cancer patients treated with TIVDAK across clinical trials. Grade ≥3 SCAR occurred in 0.5% of patients, including 1 patient who had a fatal outcome.

Monitor patients for signs or symptoms of SCAR, which include target lesions, worsening skin reactions, blistering or peeling of the skin, painful sores in mouth, nose, throat, or genital area, fever or flu-like symptoms, and swollen lymph nodes. If signs or symptoms of SCAR occur, withhold TIVDAK until the etiology of the reaction has been determined. Early consultation with a specialist is recommended to ensure greater diagnostic accuracy and appropriate management. Permanently discontinue TIVDAK for confirmed Grade 3 or 4 SCAR, including SJS.

Embryo-fetal toxicity: TIVDAK can cause fetal harm when administered to a pregnant woman. Advise patients of the potential risk to a fetus. Advise females of reproductive potential to use effective contraception during treatment with TIVDAK and for 2 months after the last dose. Advise male patients with female partners of reproductive potential to use effective contraception during treatment with TIVDAK and for 4 months after the last dose.

Adverse Reactions

Across clinical trials of TIVDAK in 425 patients with r/mCC, the most common (≥25%) adverse reactions, including laboratory abnormalities, were hemoglobin decreased (45%), PN (39%), conjunctival adverse reactions (38%), nausea (37%), fatigue (36%), aspartate aminotransferase increased (33%), epistaxis (33%), alopecia (31%), alanine aminotransferase increased (30%), and hemorrhage (28%).

innovaTV 301 Study: 250 patients with r/mCC with disease progression on or after systemic therapy

Serious adverse reactions occurred in 33% of patients receiving TIVDAK; the most common (≥2%) were urinary tract infection (4.8%), small intestinal obstruction (2.4%), sepsis, abdominal pain, and hemorrhage (each 2%). Fatal adverse reactions occurred in 1.6% of patients who received TIVDAK, including acute kidney injury, pneumonia, sepsis, and SJS (each 0.4%).

Adverse reactions leading to permanent discontinuation occurred in 15% of patients receiving TIVDAK; the most common (≥3%) were PN and ocular adverse reactions (each 6%). Adverse reactions leading to dose interruption occurred in 39% of patients receiving TIVDAK; the most common (≥3%) were ocular adverse reactions (16%) and PN (6%). Adverse reactions leading to dose reduction occurred in 30% of patients receiving TIVDAK; the most common (≥3%) were PN and ocular adverse reactions (each 10%). The ocular adverse reactions included conjunctival disorders (4.8%), keratopathy (4%), and dry eye (0.8%).

innovaTV 204 Study: 101 patients with r/mCC with disease progression on or after chemotherapy

Serious adverse reactions occurred in 43% of patients; the most common (≥3%) were ileus (6%), hemorrhage (5%), pneumonia (4%), PN, sepsis, constipation, and pyrexia (each 3%). Fatal adverse reactions occurred in 4% of patients who received TIVDAK, including septic shock, pneumonitis, sudden death, and multisystem organ failure (each 1%).

Adverse reactions leading to permanent discontinuation occurred in 13% of patients receiving TIVDAK; the most common (≥3%) were PN (5%) and corneal adverse reactions (4%). Adverse reactions leading to dose interruption occurred in 47% of patients; the most common (≥3%) were PN (8%), conjunctival adverse reactions, and hemorrhage (each 4%). Adverse reactions leading to dose reduction occurred in 23% of patients; the most common (≥3%) were conjunctival adverse reactions (9%) and corneal adverse reactions (8%).

Drug Interactions

Strong CYP3A4 inhibitors: Concomitant use with strong CYP3A4 inhibitors may increase unconjugated monomethyl auristatin E (MMAE) exposure, which may increase the risk of TIVDAK adverse reactions. Closely monitor patients for TIVDAK adverse reactions.

Use in Specific Populations

Moderate or severe hepatic impairment: MMAE exposure and adverse reactions are increased. Avoid use.

Lactation: Advise lactating women not to breastfeed during TIVDAK treatment and for at least 3 weeks after the last dose.

Please see full Prescribing Information, including BOXED WARNING for TIVDAK.

Indication

TIVDAK is indicated for the treatment of adult patients with recurrent or metastatic cervical cancer (r/mCC) with disease progression on or after chemotherapy.